
Welcome to Patriot Path
Nexus Letters for Arrhythmia and AFib
Licensed Physician, MD | Patriot Path Medical Team
Specializing in VA cardiovascular evaluations and independent medical opinions • Last updated: October 2026
Board-certified physicians specializing in VA disability documentation. Meet our clinicians → • Our review process →
A heart that skips, races, or flutters gets your attention fast. For many veterans it shows up as atrial fibrillation (AFib). That is the most common arrhythmia the VA sees. For others it is a different supraventricular arrhythmia that sends the heart into a sprint for no good reason. Sometimes you feel it. Sometimes a monitor catches it before you do.
With arrhythmia, the rating turns on the details. What does the ECG show? How many times a year did you need treatment? What was that treatment? It can also be claimed as secondary to another service-connected condition, such as sleep apnea, which opens a secondary path that is easy to miss.
Our doctors connect your arrhythmia to your service, or to a service-connected cause, in the language the VA expects. One flat fee of $1,500. The first consult is free.
How VA Rates Atrial Fibrillation and Supraventricular Arrhythmia
The VA rates AFib and most fast supraventricular rhythms under 38 C.F.R. § 4.104, Diagnostic Code 7010 (Supraventricular tachycardia). The rule itself lists atrial fibrillation as an example. The rating turns on two things. Is the rhythm confirmed by ECG? And how often did you need a treatment intervention in a year? The rule defines a 'treatment intervention' tightly. It is not just any doctor visit. Here is the rule, word for word, then what each level looks like.
"7010 Supraventricular tachycardia: Confirmed by ECG, with five or more treatment interventions per year ... 30. Confirmed by ECG, with one to four treatment interventions per year; or, confirmed by ECG with either continuous use of oral medications to control or use of vagal maneuvers to control ... 10. Note (1): Examples of supraventricular tachycardia include, but are not limited to: Atrial fibrillation, atrial flutter, sinus tachycardia, sinoatrial nodal reentrant tachycardia, atrioventricular nodal reentrant tachycardia, atrioventricular reentrant tachycardia, atrial tachycardia, junctional tachycardia, and multifocal atrial tachycardia. Note (2): For the purposes of this diagnostic code, a treatment intervention occurs whenever a symptomatic patient requires intravenous pharmacologic adjustment, cardioversion, and/or ablation for symptom relief."
| Rating | What it generally takes | Monthly pay (approx) |
|---|---|---|
| 30% | Arrhythmia confirmed by ECG, with five or more treatment interventions per year. A 'treatment intervention' means a symptomatic episode that required IV medication adjustment, cardioversion, and/or ablation. | ~$552/mo |
| 10% | Arrhythmia confirmed by ECG, with one to four treatment interventions per year; OR confirmed by ECG with continuous oral medication to control it; OR confirmed by ECG with vagal maneuvers to control it.Most Common | ~$180/mo |
DC 7010 tops out at 30%. There is no 60% or 100% row for supraventricular tachycardia itself. A higher rating usually means a different or added heart condition is in play. Examples: heart failure rated on the General Rating Formula. A pacemaker under DC 7018. A ventricular arrhythmia under DC 7011. The whole rating hangs on two phrases: 'confirmed by ECG' and 'treatment intervention.' Confirmed by ECG means the arrhythmia must be caught on a tracing. An electrocardiogram, a Holter monitor, an event monitor, or a similar tracing. A reported feeling is not enough. Treatment intervention is defined narrowly in Note (2). It counts only when a symptomatic episode required IV medication adjustment, cardioversion (shocking the rhythm back), and/or ablation (a catheter procedure to fix it). A routine medication refill or a check-up does not count. So picture a veteran on daily oral medication that keeps the rhythm quiet. No IV adjustments, no cardioversions, no ablations. That veteran usually rates 10% on the 'continuous use of oral medications to control' path. That holds even though the AFib is real and ongoing. Keep your ECG/Holter tracings, your cardioversion and ablation records, and your medication list together. They are what set the rating. One more rule from 4.104: for Diagnostic Codes 7009, 7010, 7011, and 7015, a single evaluation will be assigned under the diagnostic code that reflects the predominant disability picture. If more than one rhythm code could apply, the VA picks the one that best fits. It does not stack them.
Pay figures are approximate 2026 rates (effective December 1, 2025) for a single veteran with no dependents. Check VA.gov for current amounts.
A note on ventricular arrhythmias (DC 7011)
The rating above covers supraventricular arrhythmias (AFib, atrial flutter, SVT). Those rhythms start in the upper chambers. Ventricular arrhythmias start in the lower chambers, and they are more dangerous. So the VA rates them differently and higher, under 38 C.F.R. § 4.104, Diagnostic Code 7011 (Ventricular arrhythmias (sustained)). A 100% rating applies, verbatim, for the situations below.
- 1
Hospital-treated sustained ventricular arrhythmia
A 100% rating applies for an indefinite period from the date of inpatient hospital admission for initial medical therapy for a sustained ventricular arrhythmia, or from admission for ventricular aneurysmectomy.
- 2
An AICD in place
Having an automatic implantable cardioverter-defibrillator (AICD) in place rates 100%.
- 3
Mandatory re-exam and residuals
After that, the VA does a mandatory exam six months post-discharge. It then rates any residuals under the General Rating Formula for Diseases of the Heart (the MET-based scale).
"For an indefinite period from the date of inpatient hospital admission for initial medical therapy for a sustained ventricular arrhythmia; or, for an indefinite period from the date of inpatient hospital admission for ventricular aneurysmectomy; or, with an automatic implantable cardioverter-defibrillator (AICD) in place ... 100." - 38 C.F.R. § 4.104, Diagnostic Code 7011. If you have an AICD or a documented sustained ventricular arrhythmia, this is a different and much higher path than DC 7010. Flag it for your reviewer.
Estimate your likely arrhythmia rating (DC 7010)
This estimator is for supraventricular arrhythmias like AFib. It is a rough guide, not a rating. The VA decides your claim on your records and its own exam. Have an AICD (implantable defibrillator) or a hospital-treated sustained ventricular arrhythmia? That is rated under DC 7011 at 100%, not under this estimator.
Making a VA Disability Claim for Arrhythmia
A VA disability claim for arrhythmia needs three things to line up:
A current diagnosis, confirmed by ECG
AFib, atrial flutter, or another supraventricular arrhythmia. It must be documented on a tracing (ECG, Holter, or event monitor).
A service connection
Either the arrhythmia began in service, or it ties to an in-service cause, or it ties to another service-connected condition. This is where sleep apnea and PTSD come in.
A medical nexus
A qualified medical opinion. It says your arrhythmia is 'at least as likely as not' connected to your service, or to a service-connected cause.
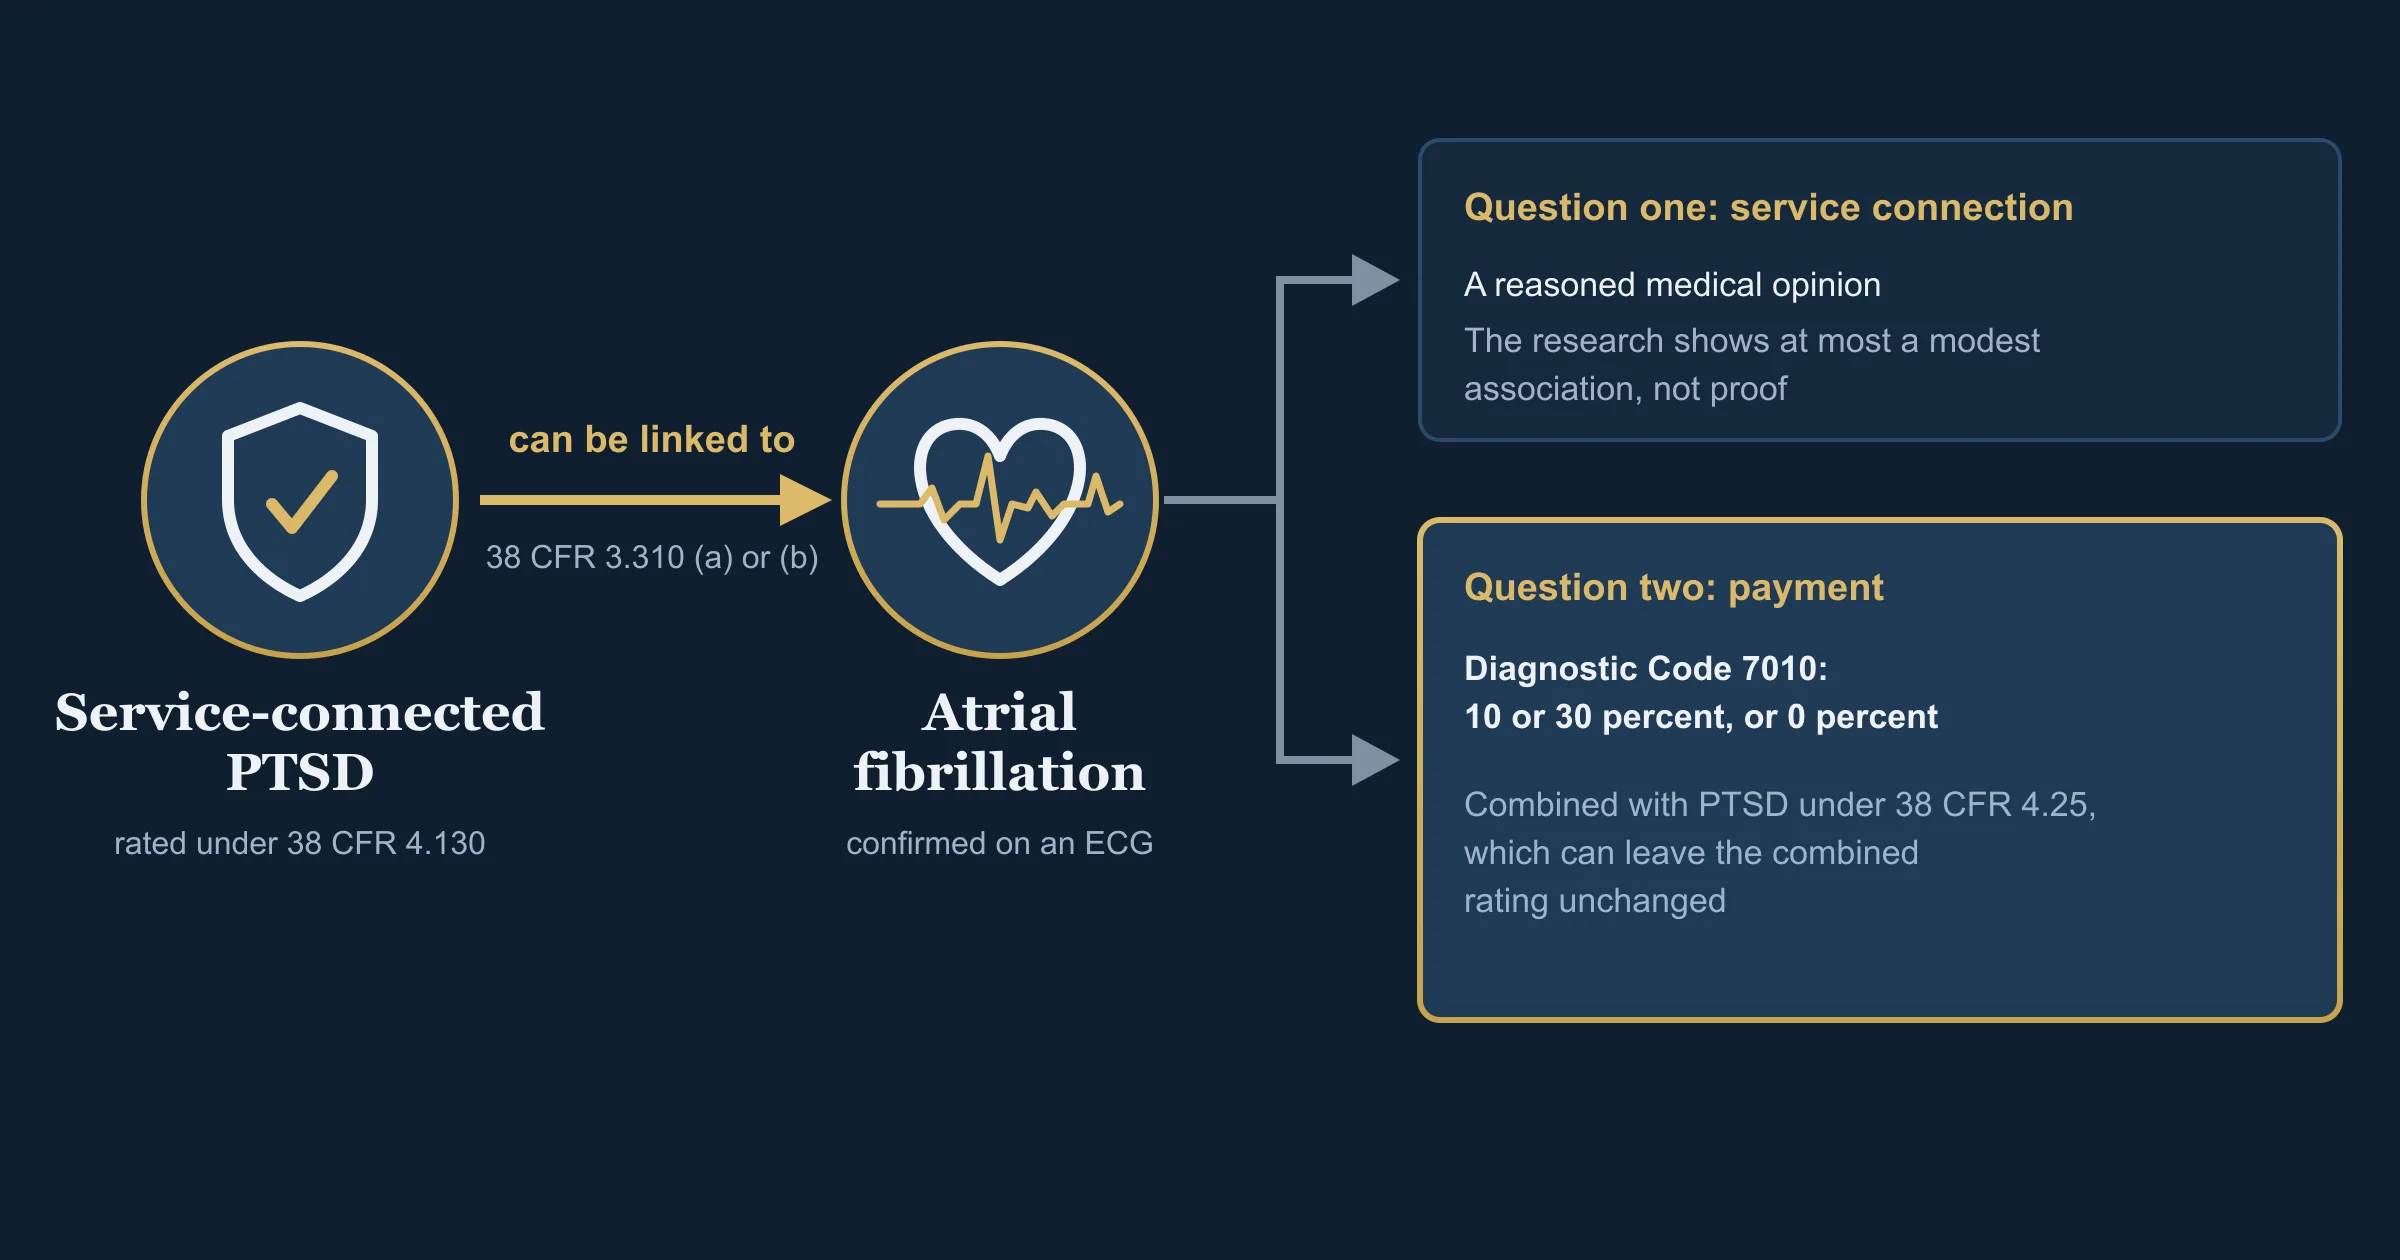
For arrhythmia, do not overlook the secondary path. Two service-connected conditions are worth checking first. The first is obstructive sleep apnea. It is strongly linked to atrial fibrillation. The link runs through repeated overnight oxygen drops and pressure changes in the chest. Is your sleep apnea already service-connected? Then AFib secondary to it can be a route to service connection. The second is PTSD. AFib has been granted secondary to PTSD in some Board decisions, but the research on the link is mixed and does not prove that PTSD causes AFib. Long-standing hypertension and other service-connected heart conditions can play a part as well. The 'at least as likely as not' standard (a 50% or better chance) comes from the benefit-of-the-doubt rule in 38 U.S.C. § 5107(b). It is carried out in 38 C.F.R. § 3.102.
How to Connect Arrhythmia to Service
There are a few ways to tie arrhythmia to your service. Where sleep apnea is already service-connected, the secondary path is worth a close look. A PTSD link is possible too, but the research behind it is mixed.
Direct connection
The arrhythmia began in or was first documented during service.
- A tracing or treatment in service. An in-service ECG showing AFib or SVT. Treatment for palpitations or a racing heart. A documented cardioversion.
- Onset soon after service. An arrhythmia that showed up in the years right after service can still support a direct claim. It takes the right medical opinion.
Secondary connection (the path many veterans miss)
Another service-connected condition caused or worsened your arrhythmia (38 C.F.R. § 3.310). These secondary links are worth checking.
- Sleep apnea. Obstructive sleep apnea is strongly linked to atrial fibrillation. The repeated oxygen drops and surges at night put stress on the heart. They are a well-documented driver of AFib. If your sleep apnea is service-connected, AFib secondary to it is worth a serious look.
- PTSD and other mental-health conditions. AFib has been granted secondary to PTSD in some Board decisions and denied in others, each binding only with regard to the specific case decided (38 CFR 20.1303). The research is mixed: one large veteran study found a small association, and a separate study of women veterans did not find a significant link. Neither is proof of cause, so the opinion has to be built on your own records. Nexus letter for AFib secondary to PTSD →
- Hypertension and heart disease. Long-standing high blood pressure can help cause arrhythmia. So can other service-connected heart conditions.
Aggravation
You had an arrhythmia before service. Service made it permanently worse (beyond its natural course).
- Worse during service. On active duty, your episodes came more often or grew more severe, or your treatment had to be stepped up. That change went beyond normal change over time.
Secondary Conditions
Arrhythmia can follow from another service-connected condition, and it can lead to others. A linked condition is rated separately only where its symptoms are distinct and no specific rule bars it. 38 C.F.R. § 4.14 bars rating the same symptoms twice, and Diagnostic Codes 7009, 7010, 7011, and 7015 get a single evaluation under whichever code reflects the predominant disability picture. Separate ratings are then combined under the combined ratings table in 38 C.F.R. § 4.25, not added, so a new rating can leave your combined number unchanged. Each link is still worth documenting.
Arrhythmia may be secondary to
- Sleep apnea. Obstructive sleep apnea is a leading driver of atrial fibrillation. It works through repeated overnight oxygen drops and pressure changes in the chest. A strong secondary path where sleep apnea is service-connected.
- PTSD. The research is mixed, with a small association in one veteran cohort and no significant link in another. That is not proof of cause, so a claim needs an opinion built on your own records. AFib secondary to PTSD →
- Hypertension. Long-standing high blood pressure strains the heart and can help cause arrhythmia.
Conditions that may be secondary to arrhythmia
- Stroke / thromboembolism. AFib raises the risk of clots and stroke. That is why many AFib patients are on blood thinners. Stroke residuals are rated under their own codes.
- Heart failure. Over time, a poorly controlled fast rhythm can weaken the heart. Heart failure is rated on the General Rating Formula for Diseases of the Heart.
- Anxiety and depression. Living with a heart-rhythm condition can help cause a mental-health condition, and that condition can be claimable. Already service-connected for PTSD? The same mental-health symptoms cannot be rated twice (38 C.F.R. § 4.14), so a new diagnosis may be rated together with your PTSD rather than separately.
What to Gather - Evidence Checklist
Gather these before you file or ask for a letter. For arrhythmia, the ECG tracing and your treatment history do the heavy lifting.
Frequently Asked Questions
How does the VA rate atrial fibrillation?
Under 38 C.F.R. 4.104, Diagnostic Code 7010 (Supraventricular tachycardia), which lists atrial fibrillation as an example. The arrhythmia must be confirmed by ECG. It rates 30% with five or more 'treatment interventions' in a year. It rates 10% with one to four interventions a year, or with continuous oral medication or vagal maneuvers to control it. DC 7010 tops out at 30%.
What counts as a 'treatment intervention' for the AFib rating?
The rule defines it narrowly. Under Note (2) of DC 7010, a treatment intervention happens only when a symptomatic episode requires IV medication adjustment, cardioversion, and/or ablation. A routine medication refill or a regular check-up does not count. That definition is the difference between the 10% and 30% levels.
Why is my AFib only rated 10% when I take medication every day?
Because daily oral medication that controls the rhythm falls under the 10% criterion ('continuous use of oral medications to control'). To reach 30% you usually need five or more defined treatment interventions in a single year. That means IV adjustments, cardioversions, or ablations. The medication keeping you stable is good for your health. But on this rating scale it sits at 10%.
Can my AFib be connected to my sleep apnea or PTSD?
Yes, it can be, on a secondary basis under 38 C.F.R. 3.310. Obstructive sleep apnea is a well-documented driver of atrial fibrillation. Is your sleep apnea already service-connected? Then AFib secondary to it can be a path to service connection. AFib has been granted secondary to PTSD in some Board decisions and denied in others, each binding only with regard to the specific case decided (38 CFR 20.1303). The research is mixed: a large veteran study found a small association and a study of women veterans found no significant one, so it does not prove cause and the opinion has to rest on your own records. That is the kind of link a nexus letter is built to show.
How are ventricular arrhythmias rated differently?
Ventricular arrhythmias start in the heart's lower chambers. They are rated under DC 7011, not DC 7010. A sustained ventricular arrhythmia treated in the hospital rates 100%. So does having an automatic implantable cardioverter-defibrillator (AICD) in place. Then comes a mandatory re-exam six months later. Residuals are rated on the General Rating Formula. If you have an AICD, this is a separate, higher path.
Do I need a nexus letter for arrhythmia?
Not always. If the arrhythmia was clearly documented and treated in service, or your VA or treating records already tie it to a service-connected condition like sleep apnea or PTSD, the record may carry it. Where that link is missing or disputed, a nexus letter gives the VA a reasoned 'at least as likely as not' medical opinion on it. That opinion is what we write.
A heart that won't keep time is still a service connection worth making.
Let our doctors write your arrhythmia nexus letter. It will meet the VA's evidence standards and support the benefits you earned.
Sources & Regulatory References
- 38 CFR 4.104, Schedule of ratings, cardiovascular system, including DC 7010 and DC 7011 (eCFR) https://www.ecfr.gov/current/title-38/section-4.104
- 38 CFR 3.310, Secondary service connection (eCFR) https://www.ecfr.gov/current/title-38/section-3.310
- 38 CFR 3.102, Reasonable doubt (eCFR) https://www.ecfr.gov/current/title-38/section-3.102
- VA disability compensation (VA.gov) https://www.va.gov/disability/
- 2026 VA disability compensation rates (VA.gov) https://www.va.gov/disability/compensation-rates/veteran-rates/
- About VA disability ratings (VA.gov) https://www.va.gov/disability/about-disability-ratings/