
VA Secondary Claims
Nexus Letter for Sleep Apnea Secondary to Kidney Disease
Medically reviewed by the Patriot Path Medical Team
Licensed MD reviewers • Last updated: November 2026
A nexus letter is the medical opinion that ties your obstructive sleep apnea to your service-connected kidney disease. The VA does not presume the link, so the claim needs medical evidence connecting the two conditions, and a nexus letter is one way to supply it. A letter sets out a physician's opinion on whether your sleep apnea is at least as likely as not caused or aggravated by your kidney disease, and the medicine behind that conclusion, such as the fluid overload that can narrow the airway at night. VA weighs it with the rest of the record, including any VA examination.
An illustrative example
David had a service-connected kidney condition that grew out of his service-connected diabetes. Over a couple of years his ankles swelled by evening and his sleep fell apart. A sleep study confirmed obstructive sleep apnea and he was put on a CPAP machine, but he assumed the two problems were unrelated, so he claimed the sleep apnea on its own.
The VA denied it. His apnea diagnosis was solid and his kidney disease was service-connected, but nothing in the file explained why the kidney disease would drive the apnea. The VA treated the sleep apnea as ordinary and unconnected to service.
A physician then wrote a nexus letter that laid out the mechanism, fluid his kidneys could no longer clear pooling in his legs by day and shifting up to his neck at night, swelling and narrowing his airway, and cited the research behind it. On the supplemental claim, the VA connected the sleep apnea to his kidney disease and granted it.
A composite we wrote to show how the pieces of this claim fit together. It is not a client or a case result, and it predicts nothing about yours.

What Sleep Apnea Secondary to Kidney Disease Means
Service connection can look like a straight line: something happened in service, and it caused a condition. A secondary claim works differently. It connects a new condition to a condition the VA already service-connected, rather than to your service directly. The rule that allows it is 38 C.F.R. 3.310.
Sleep apnea secondary to kidney disease fits this exactly. Your kidney disease is already service-connected. Your obstructive sleep apnea came later. You are asking the VA to accept that the kidney disease caused the sleep apnea, or made it worse than it would have been on its own. Aggravation counts too: if the sleep apnea came first instead, and the kidney disease made it worse, the increase can be service connected under 38 C.F.R. 3.310(b), as long as VA can establish how severe the apnea was before it worsened.
The catch is that the VA does not assume any of this. Unlike a presumptive claim, where the link is presumed, a secondary claim needs medical evidence of the link. That evidence can be a VA examiner's opinion or a private one such as a nexus letter, and VA weighs all of it.
New to these documents? Start with our primer on what a nexus letter is.
Kidney disease can itself be a secondary condition, for example secondary to service-connected diabetes or hypertension (see our guide to kidney disease secondary to hypertension), which means a chain can run from a service-connected condition, to kidney disease, to sleep apnea. Each link in that chain needs its own service connection, and a nexus letter can document more than one step.
How Kidney Disease Can Cause and Aggravate Sleep Apnea
The connection is a medical question that researchers have studied. A 2024 pooled analysis put the prevalence of sleep apnea, not limited to the obstructive type, at 57 percent across 32 studies of people with chronic kidney disease and 49 percent across 91 studies of people with kidney failure, which its authors describe as "almost 2- to 3-fold higher than that in the general population". It found prevalence "clearly linked to classic risk factors, such as age, gender and obesity, but not to the severity of CKD", and no higher prevalence on dialysis than without it, though the authors also write that "As CKD worsens, the AHI can increase", the AHI being the hourly count of breathing pauses and shallow breaths during sleep (Pisano, 2024). In Taiwan's national insurance records, people starting peritoneal dialysis had a higher adjusted risk of a new obstructive sleep apnea diagnosis than matched controls (subhazard ratio 2.34), while people starting hemodialysis did not after adjustment (0.89, not significant) (Huang, 2018). Fluid overload is one of the mechanisms researchers have proposed, and the sections below set out what the cited studies measured.
Fluid overload and the overnight fluid shift
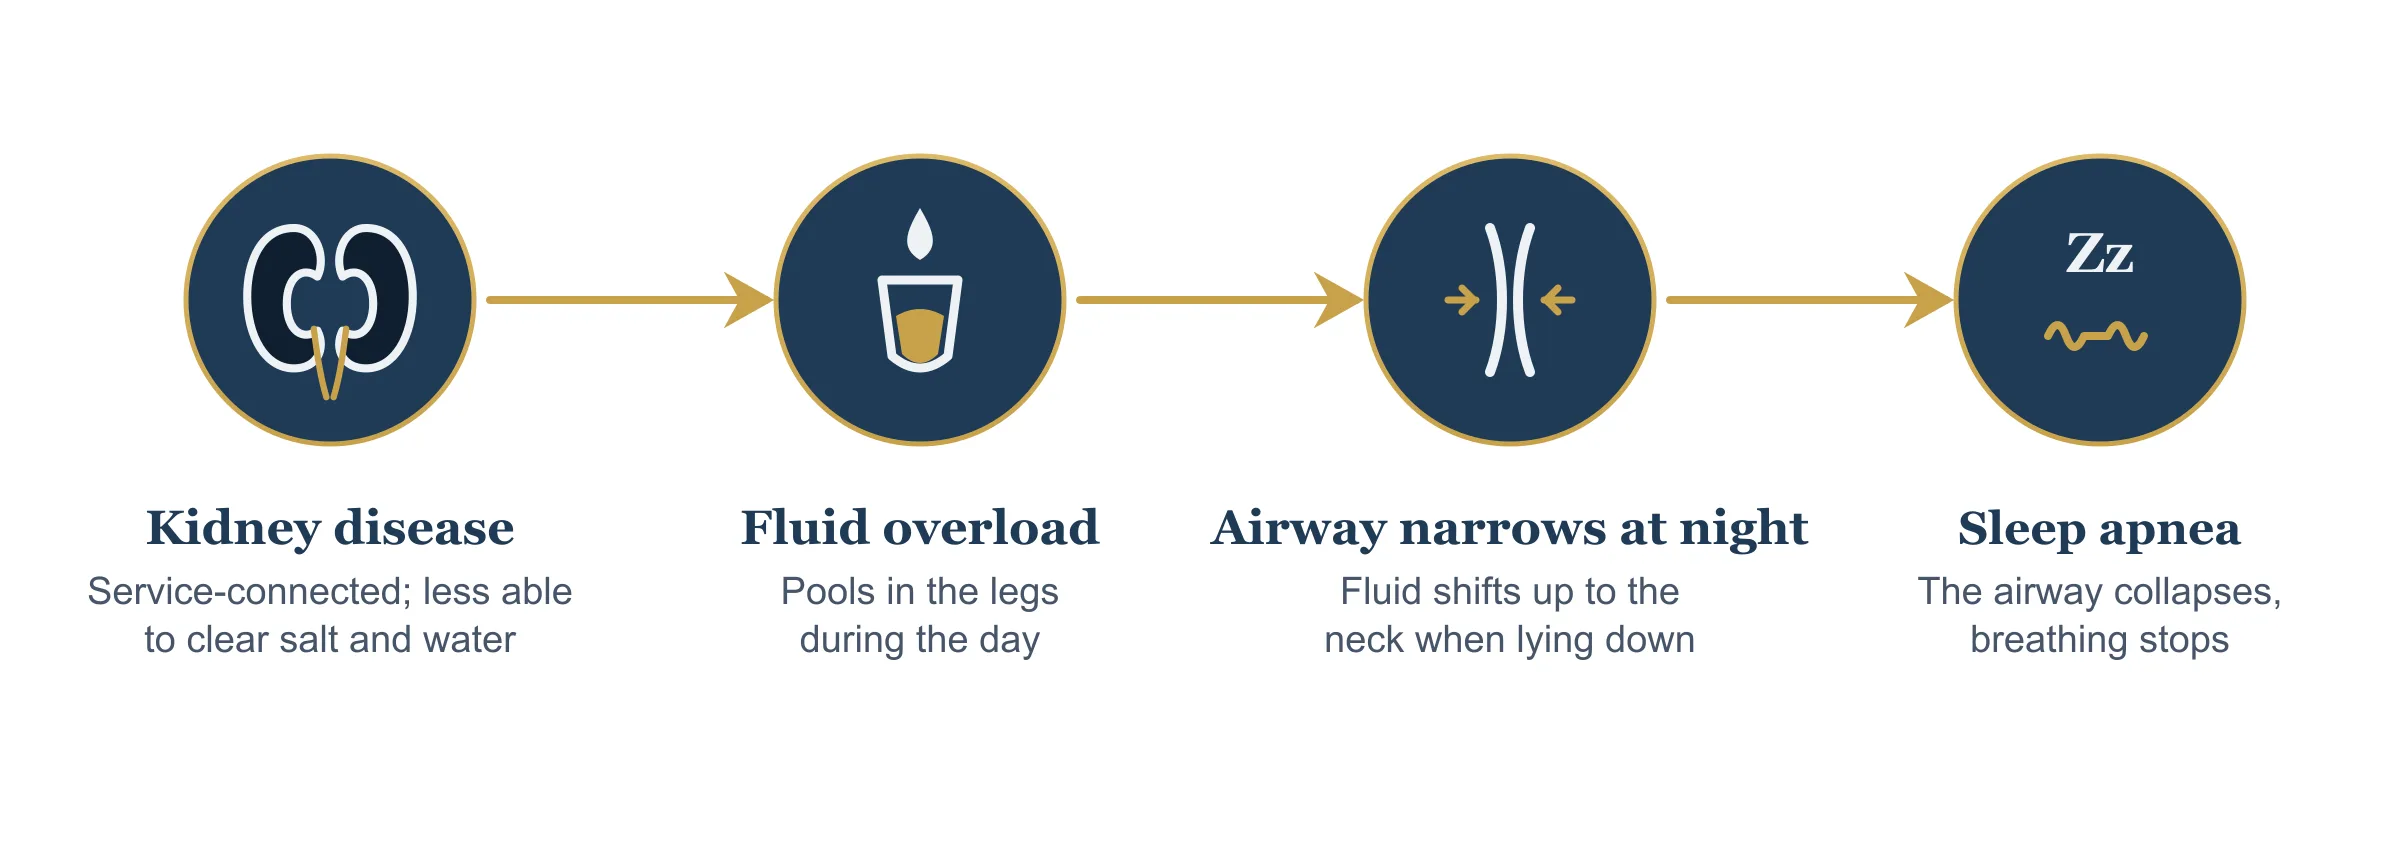
This pathway has been measured in kidney patients. When kidneys cannot fully clear sodium and water, fluid accumulates, and gravity pulls it into the legs during the day. When you lie down to sleep, that fluid shifts upward and some of it settles in the soft tissues of the neck. A swollen neck means a narrower airway, and a narrower airway is more prone to the collapse that defines an obstructive apnea event. In 26 people on hemodialysis, the more fluid left the legs overnight, the longer they spent in apneas and hypopneas (Elias, 2012). In a separate study of 17 hemodialysis patients with moderate to severe obstructive sleep apnea, severity did not change significantly on average after dialysis, but it fell in the 12 whose fluid overload fell, and the change in severity tracked the change in fluid overload (Ogna, 2015).
A buildup of waste products
As kidney function declines, waste products the kidneys normally remove build up in the blood. The accumulation of uremic toxins is among the mechanisms researchers have proposed for the link between kidney disease and sleep apnea (Pisano, 2024).
Acid buildup and breathing drive
Failing kidneys struggle to keep the blood's acid balance normal, a state called metabolic acidosis. The body compensates by changing how hard and how often it breathes, which can interact with an already unstable airway during sleep. This is a smaller, less-established contributor than the fluid shift, but it can add to the overall burden.
Which way the link runs
The direction is still being studied. In a 2024 genetic study of people of mainly European ancestry, obstructive sleep apnea showed no causal effect on any kidney measure tested; in the other direction, blood urea nitrogen, a waste product the kidneys clear, was the only kidney measure linked to sleep apnea, and chronic kidney disease itself showed no causal link. The authors conclude that the relationship "remains elusive and requires further investigation" (Hou, 2024).
For a nexus letter this matters because VA weighs the reasoning behind an opinion, not only its conclusion (M21-1 Part V, Subpart ii, Chapter 1, Section A, Block 2.e). A physician who names the pathway that fits your records, and says what the cited studies did and did not measure, gives VA reasoning it can weigh.
For the wider picture, see how the VA views the breathing problems of sleep apnea and every route to service-connecting it.
Can You Get VA Disability for Sleep Apnea Secondary to Kidney Disease?
Yes, you can. The VA does not keep a fixed list of approved secondary conditions, so what matters is not whether kidney disease appears on some official roster but whether the medical evidence connects it to your sleep apnea. For a grant, three things have to be in place, and the third is medical evidence tying the first two together, from a VA examination or a private opinion such as a nexus letter.

- 1
A current sleep apnea diagnosis
Obstructive sleep apnea confirmed by a sleep study: an in-lab polysomnogram, or a home sleep study VA's manual accepts. A CPAP prescription alone is not enough; the VA wants the study on record.
- 2
Kidney disease service-connected
Your kidney disease has to be service connected for the sleep apnea to be granted secondary to it, either already or by the time VA decides the sleep apnea claim. You can file the claims together, including one connecting the kidney disease to service-connected diabetes or hypertension.
- 3
A medical nexus opinion
A qualified opinion that your sleep apnea is at least as likely as not caused or aggravated by your kidney disease. A nexus letter is one way to supply it; a VA examiner's opinion is another.
What a Strong Nexus Letter Includes
The VA reads a nexus letter closely, and both the certainty of its conclusion and the reasoning behind it change how much weight it carries. A strong letter for this claim names the records reviewed, states your current sleep apnea diagnosis and the sleep study behind it, confirms your service-connected kidney disease, explains the medical mechanism, cites supporting research, and closes with the opinion stated as a probability, such as at least as likely as not. VA weighs the reasoning behind that conclusion and reads a medical report as a whole.
Language that meets the bar
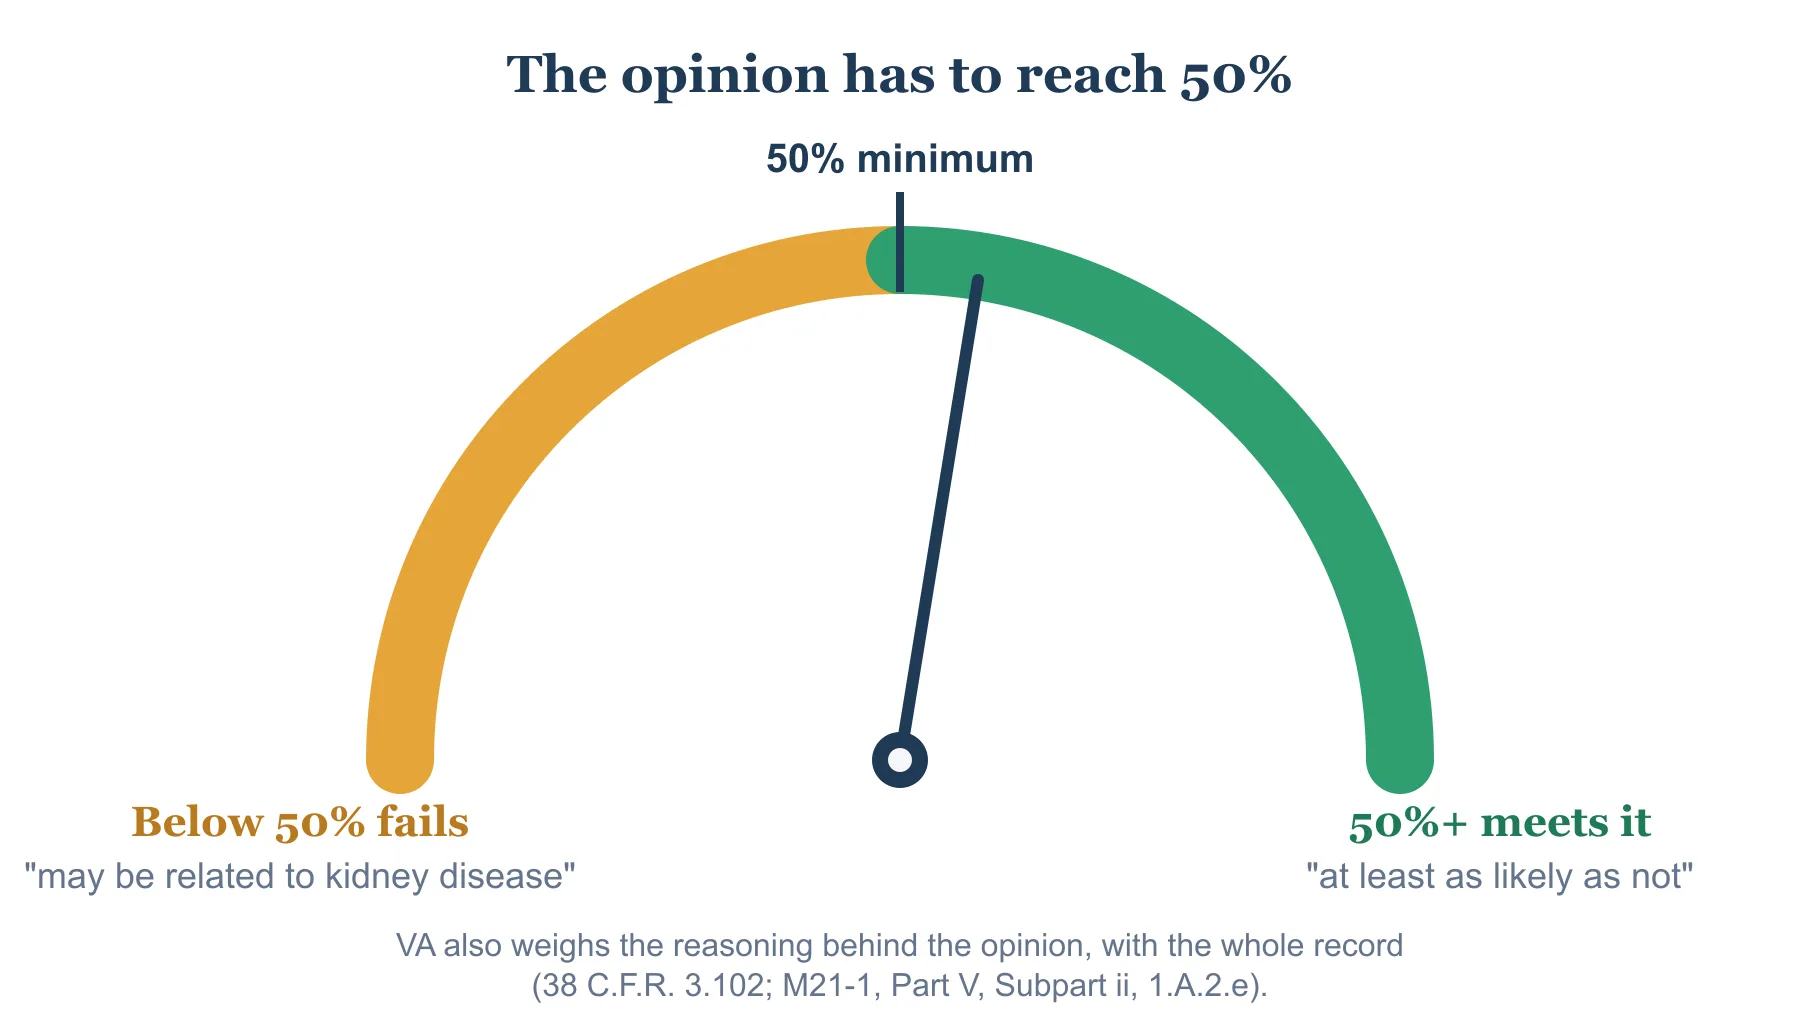
- “At least as likely as not caused or aggravated by the veteran's service-connected kidney disease” Meets the 50 percent threshold and names the secondary path. The standard to aim for.
- “More likely than not a result of the veteran's chronic kidney disease” Exceeds 50 percent; stronger than the minimum.
Language that fails
- “May be related to the veteran's kidney disease” A possibility, not a probability. Below the standard.
- “Could be associated with reduced kidney function” The word could does not meet the 50 percent bar, and the opinion has to name the service-connected condition.
Do not overlook aggravation
If your sleep apnea existed before but kidney disease made it worse, the letter should say so directly and describe the baseline. Aggravation is its own path to service connection under 38 C.F.R. 3.310(b), and a letter that documents the worsening can win even when the condition was not caused by kidney disease outright. VA will not concede aggravation unless the baseline, how severe the apnea was before the kidney disease worsened it, is established by medical evidence created before the worsening or by the earliest medical evidence created after it; an earlier sleep study, if you have one, is that kind of record. VA's manual adds that other credible evidence, including lay statements, can support the baseline, and that if no baseline can be established after VA has developed the claim, an aggravation claim must be denied (M21-1 Part V, Subpart ii, Chapter 2, Section D, Blocks 1.c and 1.f).
What a Kidney-to-Sleep-Apnea Nexus Letter Looks Like
Here is what the pieces look like for this specific claim. This is an illustration of the structure, not a template to copy; a real letter is written from your records by the physician who reviews them.
Records reviewed
I have reviewed the veteran's VA rating decision service-connecting chronic kidney disease, the polysomnography report dated [date] confirming obstructive sleep apnea, the CPAP prescription and compliance data, and the nephrology records documenting reduced kidney function and fluid retention.
Current diagnosis
The veteran carries a current diagnosis of obstructive sleep apnea, confirmed by sleep study with an apnea-hypopnea index of [value], and is prescribed CPAP therapy.
The medical rationale
Chronic kidney disease impairs the clearance of sodium and water. The resulting fluid overload accumulates in the lower extremities during the day and shifts rostrally to the neck when the veteran is recumbent at night, narrowing the upper airway and increasing its tendency to collapse. This mechanism has been studied in patients on hemodialysis, where a larger overnight shift of fluid out of the legs went with more time in apneas and hypopneas (Elias, 2012) and the change in apnea severity after dialysis followed the change in fluid overload (Ogna, 2015).
The opinion
It is my opinion that the veteran's obstructive sleep apnea is at least as likely as not caused or aggravated by his service-connected chronic kidney disease.
Notice that the opinion states its conclusion as a probability, and that the rationale names a specific, documented mechanism rather than asserting a link. VA's manual lists the reasoning employed by the physician and the degree of certainty among the key elements it considers when weighing medical evidence (M21-1 Part V, Subpart ii, Chapter 1, Section A, Block 2.e).
Reasons These Claims Can Get Denied
A sleep apnea secondary to kidney disease claim can be denied for gaps that can be fixed. Here are four, and each is something you and your provider can address before VA decides the claim.
No sleep study on file
A CPAP prescription or a doctor's note is not enough. VA's manual tells raters not to establish service connection for sleep apnea that a sleep study has not confirmed, and it accepts a home sleep study only if it was clinically determined that you could be evaluated that way and a competent medical provider evaluated the results. Get the study on record before VA decides the claim.
The kidney disease is not yet service-connected
A secondary claim has to attach to a service-connected condition. If your kidney disease is not service connected by the time VA decides the sleep apnea claim, the sleep apnea has nothing to attach to. You do not have to wait to file: the kidney claim can go in with this one, and VA's manual bases the effective date of a secondary grant on the date the claim it is granted on was filed (M21-1 Part V, Subpart ii, Chapter 4, Section A, Block 3.f).
The opinion used weak language
Phrases like may be related or could be connected express possibility, and 38 C.F.R. 3.102 describes reasonable doubt as one "within the range of probability as distinguished from pure speculation or remote possibility". State the conclusion as a probability, such as at least as likely as not, and give the reasoning: VA weighs the physician's reasoning and degree of certainty and reads a report as a whole (M21-1 Part V, Subpart ii, Chapter 1, Section A, Blocks 2.e and 3.g).
No mechanism was explained
An opinion that simply asserts a link, without explaining how kidney disease affects the airway, lacks the rationale VA's manual requires for any medical opinion (M21-1 Part V, Subpart ii, Chapter 1, Section A, Block 3.g). A letter that sets out the fluid-overload pathway and what the cited studies measured gives VA reasoning to weigh.
What to Give Your Provider
A nexus letter is only as strong as the records behind it. Bring these so the physician can write from evidence rather than assumption.
The core file
- Your kidney disease service-connection decisionThe VA letter or rating showing kidney disease is service-connected, with the effective date. If it is secondary to diabetes or hypertension, bring that decision too.
- Your sleep studyThe polysomnogram, or accepted home sleep study, confirming obstructive sleep apnea and its severity (the AHI). VA will not service connect sleep apnea without one.
- CPAP prescription and compliance dataYour device prescription and any usage or compliance records, which show the treatment and its necessity.
- Your kidney treatment recordsNephrology notes, lab work such as eGFR and creatinine, any dialysis records, and notes on fluid retention or swelling, which establish the kidney disease behind the link.
What strengthens it
- A timelineRoughly when your kidney problems and your sleep problems each began, so the physician can line them up.
- Lay statementsShort notes from a partner or family member about snoring, choking, gasping, witnessed pauses in breathing, or worsening leg swelling.
VA Rating for Sleep Apnea (Diagnostic Code 6847)
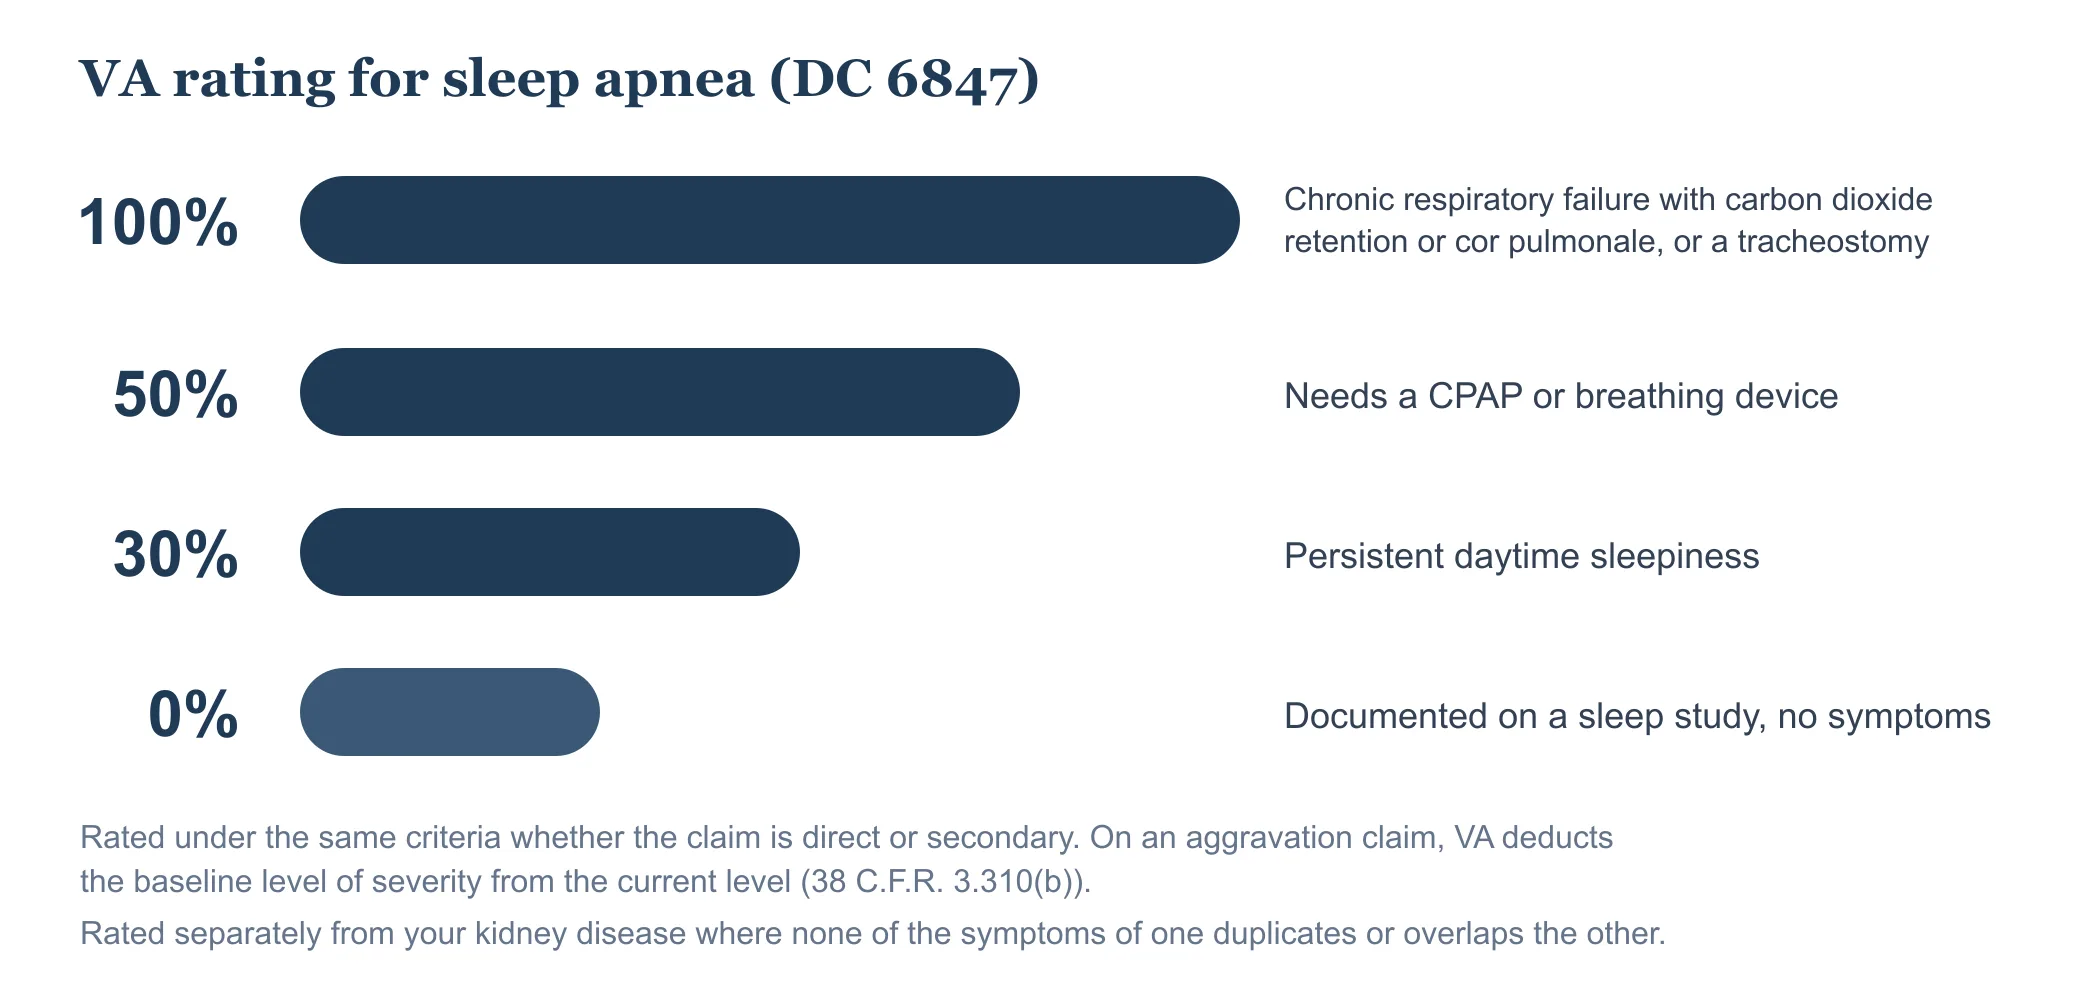
Once sleep apnea is service-connected, the VA rates it under 38 C.F.R. 4.97, Diagnostic Code 6847. The rating turns on how the condition is treated and how severe it is, not on what caused it, so a secondary claim is rated under the same criteria as a direct one. On an aggravation claim under 38 C.F.R. 3.310(b), VA deducts the baseline level of severity from the current level.
| Rating | What it takes |
|---|---|
| 100% | Chronic respiratory failure with carbon dioxide retention or cor pulmonale, or requires a tracheostomy. |
| 50% | Requires use of a breathing assistance device. The code names a CPAP machine as an example, and VA also accepts other qualifying devices, including APAP and BiPAP machines, nasal dilators and stents, and certain oral appliances. |
| 30% | Persistent day-time hypersomnolence, meaning ongoing excessive daytime sleepiness. |
| 0% | Asymptomatic but with documented sleep disorder breathing. |
The 50 percent level turns on whether a breathing assistance device is medically necessary, not on whether you happen to own or use one. VA treats necessity as a medical question, and its adjudication manual is explicit that a veteran who does not use a device as prescribed does not lose the rating for that reason alone. Use of a device without a medical determination that it is necessary does not qualify. So what matters is the medical determination in your records, not the receipt for the machine. On combining the two, sleep apnea and kidney disease carry separate diagnostic codes, kidney disease being evaluated under the genitourinary rules at 38 C.F.R. 4.115a and 4.115b, and 38 C.F.R. 4.14 permits separate evaluations only where none of the symptomatology for one condition duplicates or overlaps the other, the test stated in Esteban v. Brown. A separate evaluation for each is therefore defensible, but it is not automatic, and overlapping symptoms can be evaluated only once.
For the full picture on sleep apnea ratings, sleep studies, and every route to service connection, see our guide to sleep apnea and VA disability.
Is Your Secondary Claim Ready?
Check your file
Tick each item that matches your file today. Nothing here is scored. The first item asks whether VA has already settled the link, the next two are requirements a letter cannot supply, and the last two name the question a physician's opinion answers.
Nothing is ticked yet. The result appears here as you tick the items that match your file.
Finding a Provider to Write the Letter
Any licensed physician can write a nexus letter, but the ones the VA takes seriously come from providers who can explain the mechanism and cite the literature, not just state an opinion. Your VA provider must assist when you ask, and VHA policy contemplates VA clinicians giving causality opinions. That same policy says "VHA providers often do not have access to military medical records, and may not be familiar with all the health issues specific to military service, such as environmental exposure" (VHA Directive 1134(3), paragraph 5.d.(1)(b)1), which is one reason a veteran may also seek an independent medical opinion from an outside physician.
Patriot Path physicians write letters built for this exact claim: records reviewed, the kidney-to-sleep-apnea mechanism, supporting research, and the opinion stated as a probability, with its reasoning. One flat fee of $1,500, and the first consultation is free.
Not sure who qualifies? See our breakdown of who can write a nexus letter, what belongs in one in our guide to nexus letter requirements, and our flat-rate pricing.
See the full scope of our nexus letter services and how the process works.
Why Act Sooner Rather Than Later
Unless another rule applies, the effective date is the date VA receives the claim or the date entitlement arose, whichever is later (38 C.F.R. 3.400), so a claim you put off is money left on the table. Filing now, even while you gather evidence, protects an earlier effective date.
It also helps your record. Sleep apnea documented over time, alongside your kidney disease and its fluid retention, makes the connection easier for a physician to establish and harder for the VA to dismiss. Kidney disease can progress, and a record that follows both conditions over time gives a physician dated evidence to work from. And when the evidence is roughly balanced, the law requires the VA to decide in your favor (38 U.S.C. 5107), which is exactly the edge a well-built nexus letter is meant to create.
Turn Your Diagnosis Into a Documented Claim
Your sleep study and your kidney disease are both on the record. Our physicians can tell you whether an honest opinion on the link between them can be supported, and write it if it can.
Frequently Asked Questions
Is sleep apnea linked to kidney disease?
Yes, they are associated. A 2024 pooled analysis found sleep apnea, not limited to the obstructive type, in 57 percent of people with chronic kidney disease across 32 studies and in 49 percent of people with kidney failure across 91 studies (Pisano, 2024). Fluid overload is one proposed pathway: in 17 hemodialysis patients with moderate to severe obstructive sleep apnea, average apnea severity did not change significantly after dialysis, but the change in severity tracked the change in fluid overload (Ogna, 2015). A genetic study in people of mainly European ancestry found no causal effect of obstructive sleep apnea on kidney function and no causal link from chronic kidney disease itself to sleep apnea, though genetically predicted higher blood urea nitrogen was associated with it (Hou, 2024). Whether your kidney disease caused or worsened your sleep apnea is a question for a medical opinion on your own records.
Can you claim sleep apnea secondary to kidney disease?
Yes. Sleep apnea can be service-connected as secondary to kidney disease when a medical opinion shows your kidney disease at least as likely as not caused or aggravated your sleep apnea; for aggravation, VA also needs a baseline showing how severe the apnea was before the kidney disease worsened it. The kidney disease has to be service connected for VA to grant the sleep apnea as secondary to it, though the two can be claimed together, and a sleep study has to confirm the apnea. The medical opinion can come from a VA examination or from a private physician's nexus letter.
Does the VA automatically connect sleep apnea to kidney disease?
No. There is no presumption linking sleep apnea to kidney disease, so the link has to be shown by medical evidence, which can come from a VA examination or from a private opinion such as a nexus letter. The standard is not proof: when the positive and negative evidence are in approximate balance, VA must give the veteran the benefit of the doubt (38 U.S.C. 5107(b)).
Does my kidney disease need to be service-connected first?
For the sleep apnea to be granted as secondary to it, yes, but you do not have to wait to file. Sleep apnea can be service connected on this basis only once the kidney disease is service connected, and the kidney claim, including one connecting the kidney disease to service-connected diabetes or hypertension, can be filed with the sleep apnea claim. VA's manual bases the effective date of a secondary grant on the date the claim it is granted on was filed, and no earlier than the effective date for the condition it is secondary to (M21-1 Part V, Subpart ii, Chapter 4, Section A, Blocks 3.f and 3.g), so waiting to file can cost you an earlier effective date.
What evidence does the VA need for sleep apnea?
The VA requires a diagnosis confirmed by a sleep study; a CPAP prescription on its own is not enough. A home sleep study counts only if a clinician decided you could be tested that way and a competent medical provider evaluated the results. Bring the study, your CPAP records, your kidney treatment history including labs and any dialysis records, and lay statements about snoring, gasping, or witnessed pauses in breathing. A medical opinion, from a VA examination or a private nexus letter, then addresses whether this evidence links your sleep apnea to your service-connected kidney disease.
What VA rating does sleep apnea get?
Sleep apnea is rated under Diagnostic Code 6847 at 0, 30, 50, or 100 percent. The 50 percent level applies when a breathing assistance device, such as a CPAP machine, is medically necessary. It is rated under the same criteria whether the claim is direct or secondary; on an aggravation claim under 38 C.F.R. 3.310(b), VA deducts the baseline level of severity from the current level. It carries a diagnostic code separate from kidney disease, though separate evaluations hold only where the symptoms of one condition do not overlap the other.
Can I claim aggravation if I already had sleep apnea?
Yes. Under 38 C.F.R. 3.310(b), you can be service-connected for the amount your kidney disease worsened a condition you already had. VA will not concede aggravation without a baseline: medical evidence of how severe the sleep apnea was before the kidney disease worsened it, from before the worsening or the earliest record after it. VA's manual also lets other credible evidence, including lay statements, support the baseline, and VA has to try to develop it before denying on that ground (M21-1 Part V, Subpart ii, Chapter 2, Section D, Blocks 1.c and 1.f). The nexus letter should describe your baseline and how it changed, so the VA can see the aggravation rather than treating the sleep apnea as pre-existing and unrelated.
What does it cost, and how do we start?
Patriot Path charges $1,500 flat for a nexus letter, and the first consultation is free. Book a consultation and we will tell you honestly whether a letter can help your sleep apnea secondary to kidney disease claim. The fee is due before your letter is drafted, and if our clinician reviews your file and concludes an honest nexus opinion cannot be supported, you get your money back before drafting starts.
Related guides
- How a nexus letter fits into your claimThe full overview, start to finish.
- Nexus letter for a secondary conditionThe general guide to secondary VA claims.
- What a nexus letter must includeThe elements the VA looks for.
- Nexus letter exampleSee the framework on a finished letter.
- Who can write a nexus letterWhich providers the VA takes seriously.
- Sleep apnea and VA disabilityRatings, sleep studies, and secondary conditions.
- Sleep apnea nexus letters: the complete guideWhat the letter must say, how to get one, and what it costs.
- Sleep apnea secondary to diabetesSleep apnea claimed secondary to diabetes directly, without the kidney step.
- Kidney disease secondary to hypertensionConnecting the kidney disease itself to service-connected hypertension, a claim you can file with this one.
- Sleep apnea secondary to GERDA related secondary sleep apnea claim.
- Sleep apnea secondary to PTSDAnother secondary sleep apnea path.
Citations & References
- 38 CFR 3.310, Secondary service connection and aggravation (eCFR) https://www.ecfr.gov/current/title-38/part-3/section-3.310
- 38 CFR 4.97, Schedule of ratings, respiratory system, including DC 6847 sleep apnea (eCFR) https://www.ecfr.gov/current/title-38/part-4/section-4.97
- 38 CFR 4.115a, Ratings of the genitourinary system, renal dysfunction (eCFR) https://www.ecfr.gov/current/title-38/part-4/section-4.115a
- 38 CFR 4.115b, Schedule of ratings, genitourinary system, where kidney conditions are evaluated (eCFR) https://www.ecfr.gov/current/title-38/part-4/section-4.115b
- 38 CFR 3.102, Reasonable doubt (eCFR) https://www.ecfr.gov/current/title-38/section-3.102
- 38 CFR 3.159, VA assistance in developing claims, including medical examinations and opinions (eCFR) https://www.ecfr.gov/current/title-38/section-3.159
- 38 CFR 3.400, Effective dates (eCFR) https://www.ecfr.gov/current/title-38/section-3.400
- 38 CFR 4.14, Avoidance of pyramiding (eCFR) https://www.ecfr.gov/current/title-38/section-4.14
- 38 U.S.C. 5107, Claimant responsibility and benefit of the doubt (Cornell LII) https://www.law.cornell.edu/uscode/text/38/5107
- VA disability, evidence needed to support your claim (VA.gov) https://www.va.gov/disability/how-to-file-claim/evidence-needed/
- M21-1, Part V, Subpart iii, Chapter 4, Section A, Blocks 2.a to 2.d, sleep studies and breathing devices (VA KnowVA) https://www.knowva.ebenefits.va.gov/system/templates/selfservice/va_ssnew/help/customer/locale/en-US/portal/554400000001018/content/554400000180967/M21-1-Part-V-Subpart-iii-Chapter-4-Section-A-Respiratory-Conditions
- M21-1, Part V, Subpart ii, Chapter 2, Section D, Blocks 1.b, 1.c, 1.f and 1.g, causation, aggravation and the baseline (VA KnowVA) https://www.knowva.ebenefits.va.gov/system/templates/selfservice/va_ssnew/help/customer/locale/en-US/portal/554400000001018/content/554400000180484/M21-1-Part-V-Subpart-ii-Chapter-2-Section-D-Secondary-Service-Connection-SC-and-Aggravation-of-Non-Service-Connected-NSC-Disabilities
- M21-1, Part V, Subpart ii, Chapter 4, Section A, Blocks 3.f and 3.g, effective dates for secondary service connection (VA KnowVA) https://www.knowva.ebenefits.va.gov/system/templates/selfservice/va_ssnew/help/customer/locale/en-US/portal/554400000001018/content/554400000180492/M21-1-Part-V-Subpart-ii-Chapter-4-Section-A-Effective-Dates
- M21-1, Part V, Subpart ii, Chapter 1, Section A, Blocks 2.e and 3.g, weighing medical opinions (VA KnowVA) https://www.knowva.ebenefits.va.gov/system/templates/selfservice/va_ssnew/help/customer/locale/en-US/portal/554400000001018/content/554400000014383/M21-1-Part-V-Subpart-ii-Chapter-1-Section-A-Principles-of-Reviewing-and-Weighing-Evidence
- M21-1, Part V, Subpart ii, Chapter 3, Section D, Block 2.b, pyramiding and the Esteban note (VA KnowVA) https://www.knowva.ebenefits.va.gov/system/templates/selfservice/va_ssnew/help/customer/locale/en-US/portal/554400000001018/content/554400000180489/M21-1-Part-V-Subpart-ii-Chapter-3-Section-D-Evaluating-Disabilities
- VHA Directive 1134(3), Provision of Medical Statements and Completion of Forms by VA Health Care Providers (VA.gov PDF) https://www.va.gov/vhapublications/ViewPublication.asp?pub_ID=4300
- Pisano A, et al. Sleep apnoea syndrome prevalence in chronic kidney disease and end-stage kidney disease patients: a systematic review and meta-analysis. Clin Kidney J. 2024 (PMC) https://pmc.ncbi.nlm.nih.gov/articles/PMC10768783/
- Ogna A, et al. Obstructive sleep apnea severity and overnight body fluid shift before and after hemodialysis. Clin J Am Soc Nephrol. 2015 (PMC) https://pmc.ncbi.nlm.nih.gov/articles/PMC4455216/
- Elias RM, et al. Rostral overnight fluid shift in end-stage renal disease: relationship with obstructive sleep apnea. Nephrol Dial Transplant. 2012 (PubMed) https://pubmed.ncbi.nlm.nih.gov/22058175/
- Huang ST, et al. Risk, severity, and predictors of obstructive sleep apnea in hemodialysis and peritoneal dialysis patients. Int J Environ Res Public Health. 2018 (PMC) https://pmc.ncbi.nlm.nih.gov/articles/PMC6267173/
- Hou Y, et al. Causal effects of obstructive sleep apnea on chronic kidney disease and renal function: a bidirectional Mendelian randomization study. Front Neurol. 2024 https://www.frontiersin.org/journals/neurology/articles/10.3389/fneur.2024.1323928/full